
Avascular Necrosis (AVN) Treatment in Navi Mumbai
Dr. Abhay Chhallani, Orthopaedic and Joint Replacement Surgeon, Nerul West, Seawoods, Navi Mumbai
Avascular necrosis (AVN), also known as osteonecrosis, is a condition in which reduced blood supply damages bone tissue. Over time, the affected bone may weaken and collapse, causing damage to the joint. The hip is one of the most commonly affected areas, particularly the femoral head, which forms the ball of the hip joint. AVN can also affect the knee, shoulder and other bones.
The right treatment depends on how much damage has occurred and whether the bone has started to collapse. Some patients with early-stage AVN may be suitable for treatment that aims to preserve the natural hip. When the joint is severely damaged, hip replacement surgery may be considered.
Dr. Abhay Chhallani provides orthopaedic evaluation and guidance for patients seeking AVN hip treatment in Nerul, Navi Mumbai. After reviewing your symptoms and scan reports, he can explain the available treatment options and help you understand which approach may be suitable for your condition.
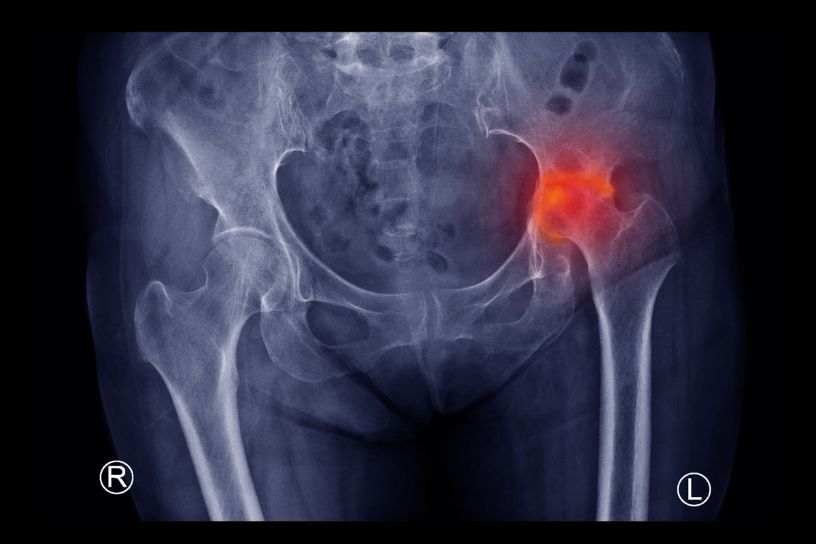
AVN at a Glance
- What is AVN? Damage to bone tissue associated with reduced blood supply.
- Most commonly affected joint: The hip, especially the femoral head.
- Common AVN causes: Corticosteroid use, heavy alcohol consumption, certain blood disorders and hip injuries.
- Common AVN symptoms: Deep groin pain, hip pain while walking and restricted movement.
- Key diagnostic test: MRI is highly sensitive for detecting early avascular necrosis.
- Why early diagnosis matters: Treatment may have a better chance of preserving the natural joint before significant collapse occurs.
- AVN treatment options: Observation, activity modification, pain management, selected joint-preserving procedures and total hip replacement.
What Is Avascular Necrosis of the Hip?
Bone is living tissue that needs a continuous blood supply to stay healthy and repair minor damage. In avascular necrosis of the hip, blood flow to a section of bone becomes inadequate, causing bone cells to die.
The condition commonly affects the femoral head, which fits into the socket of the pelvis and allows the hip to move smoothly. When the affected bone becomes weaker, it may no longer support the joint surface properly.
As hip AVN progresses, small fractures can develop beneath the cartilage. The femoral head may then flatten or collapse, damaging the cartilage and potentially leading to secondary hip arthritis.
AVN does not progress at the same rate in everyone. Some areas of bone damage remain stable, while others worsen over time. The size and location of the affected area, the stage of the condition and the presence of joint collapse all influence treatment decisions.
What Causes Avascular Necrosis of the Hip?
There is no single cause of avascular necrosis (AVN). The condition may develop after an injury or in association with medical conditions and other factors that affect blood flow to the bone.
Common causes and risk factors include:
- Hip fracture or dislocation: An injury can damage the blood vessels supplying the femoral head.
- Corticosteroid use: Long-term or high-dose steroid treatment is associated with an increased risk of AVN in some patients.
- Heavy alcohol consumption: Prolonged heavy drinking is associated with an increased risk of bone damage and AVN.
- Sickle cell disease: Abnormal red blood cells can obstruct small blood vessels and affect circulation.
- Autoimmune conditions: Conditions such as lupus may be associated with AVN, including through their treatment.
- Blood clotting disorders: Certain conditions can interfere with normal blood flow through small vessels.
- Other medical treatments: Radiation therapy and some other treatments may be associated with bone damage, depending on the circumstances.
Sometimes, doctors cannot identify a definite cause. This is known as idiopathic AVN.
Although AVN is often diagnosed in adults, younger people can also develop the condition. A person’s medical history, symptoms and risk factors help determine whether further investigation is needed.
Types of Avascular Necrosis
Avascular necrosis is generally classified according to its cause.
Traumatic AVN
Traumatic avascular necrosis develops after an injury that damages the blood supply to the bone. A fracture of the femoral neck or a hip dislocation can increase the risk of AVN affecting the femoral head.
Non-Traumatic AVN
Non-traumatic AVN develops without a direct injury. It may be associated with long-term corticosteroid use, heavy alcohol consumption, sickle cell disease, autoimmune conditions and certain blood disorders.
Idiopathic AVN
Idiopathic avascular necrosis refers to cases in which the underlying cause remains unknown despite an appropriate medical evaluation.
Identifying the possible cause helps guide treatment and risk-factor management. Because AVN can affect both hips, the doctor may recommend assessment of the opposite hip when clinically appropriate.
Why Are Steroids and Alcohol Associated With AVN?
Corticosteroid Use and Avascular Necrosis
Corticosteroids are important medicines used to manage conditions such as asthma, autoimmune diseases and severe inflammation. However, prolonged or high-dose corticosteroid use is associated with an increased risk of avascular necrosis in some patients.
The exact mechanisms are complex and may involve changes in fat metabolism, pressure inside the bone and blood flow through small vessels.
If you have taken corticosteroids and develop persistent hip or groin pain, discuss your symptoms and medical history with your doctor.
Never stop prescribed corticosteroids or change your dosage without medical advice. Your treating doctor can assess your medication and advise you on the appropriate next steps.
Alcohol Consumption and AVN
Heavy, long-term alcohol consumption is associated with an increased risk of hip AVN. Changes in fat metabolism and bone health may contribute to the condition.
Reducing or avoiding alcohol may help address this risk factor, but it cannot reverse established bone damage. If you have already been diagnosed with AVN, your treatment plan should be based on the extent of bone involvement and your overall health.
Who Is at Higher Risk of AVN?
You may need medical assessment if you have persistent hip pain along with any of the following risk factors:
- A history of long-term or high-dose steroid use.
- Regular heavy alcohol consumption.
- A previous hip fracture or dislocation.
- Sickle cell disease or certain blood clotting disorders.
- Lupus or another autoimmune condition.
- A previous diagnosis of AVN in one hip.
- A medical condition that may affect blood circulation or bone health.
Having one of these risk factors does not automatically mean that you will develop AVN. However, persistent symptoms should be checked rather than dismissed as routine joint pain.
Symptoms of Avascular Necrosis of the Hip
AVN hip symptoms can begin gradually. During the early stages, the discomfort may be mild or occur only during certain activities. As the condition progresses, pain may become more frequent and interfere with everyday movement.
Common symptoms of avascular necrosis of the hip include:
- Deep pain in the groin or hip.
- Hip pain while walking, standing or climbing stairs.
- Pain that spreads to the thigh, buttock or knee.
- Stiffness and reduced hip movement.
- Limping or difficulty bearing weight.
- Difficulty putting on shoes or socks.
- Pain at rest or during the night in more advanced cases.
Some people experience few symptoms during early AVN. The absence of severe pain does not necessarily mean that the bone is unaffected.
Why Does AVN Cause Hip Pain?
Pain can develop because of changes within the bone, inflammation and increased pressure in the affected area. As avascular necrosis progresses, small fractures or collapse of the femoral head may damage the joint surface.
This can make movement increasingly painful and affect walking, sleep, work and daily activities.
Hip pain can have several causes, so symptoms alone cannot confirm AVN. A clinical examination and appropriate imaging are important for identifying the underlying problem.
When Should You See a Doctor?
Arrange an orthopaedic assessment if hip or groin pain continues for more than two to three weeks, particularly if you have a history of corticosteroid use, heavy alcohol consumption, a hip injury or a medical condition associated with AVN.
An MRI for AVN may be recommended if the condition is suspected even when X-rays appear normal.
Seek urgent medical assessment if you develop sudden severe hip pain, cannot bear weight after an injury or experience rapidly worsening symptoms.
How Is AVN Diagnosed?
AVN diagnosis involves reviewing your symptoms, medical history and imaging results. The aim is to identify the affected area, determine the extent of bone damage and establish whether the femoral head has collapsed.
1. Medical History and Clinical Examination
The doctor will ask about your pain, activity limitations, previous injuries, medication use and relevant medical conditions.
The examination may include checking hip movement, tenderness, walking pattern and your ability to bear weight.
2. X-Ray for AVN
An X-ray of the hip helps assess the joint structure and identify changes such as flattening of the femoral head, bone collapse or secondary arthritis.
However, X-rays may appear normal during early-stage AVN. A normal X-ray does not always rule out the condition.
3. MRI for Avascular Necrosis
An MRI of the hip is highly sensitive for detecting early AVN. It can help identify the location and extent of bone involvement before changes become visible on X-rays.
MRI findings also help the doctor assess the stage of the condition and discuss suitable treatment options.
4. Assessment of the Opposite Hip
Bilateral AVN, which means AVN affecting both hips, can occur. Depending on your symptoms, medical history and initial findings, the doctor may recommend imaging of the opposite hip.
Bring previous X-rays, MRI scans, medical reports and a list of current medicines to your consultation.
Stages of Avascular Necrosis
AVN stages are classified using systems such as ARCO and Ficat. These systems assess the extent of bone damage and structural changes, but their stages do not correspond exactly to one another.
The following table provides a simplified overview.
| Stage or Condition | What It Means | General Treatment Considerations |
|---|---|---|
| Early-Stage AVN Without Collapse | Bone damage is present, but the femoral head remains structurally intact. | Monitoring and selected joint-preserving treatments may be considered. |
| AVN With Structural Damage or Early Collapse | The femoral head begins to crack, flatten, or lose its normal shape. | Treatment depends on the extent of damage and symptoms. |
| Advanced AVN With Joint Damage | Significant collapse and secondary arthritis may be present. | Total hip replacement may be considered when clinically appropriate. |
The precise stage of AVN should be established by reviewing imaging findings and conducting a clinical examination. A stage number alone does not determine the best treatment.
Early identification matters because some joint-preserving procedures for AVN are generally more suitable before substantial collapse occurs.
AVN Treatment Options in Navi Mumbai
The right AVN treatment in Navi Mumbai depends on the stage of the condition, the size and location of the damaged area, whether the femoral head has collapsed, your age and your activity requirements.
Treatment may focus on managing pain, reducing stress on the affected hip, preserving the natural joint where possible or replacing a severely damaged joint.
Dr. Abhay Chhallani evaluates the available options according to the patient’s condition. Not every patient needs surgery, and not every patient is suitable for a joint-preserving procedure.
Non-Surgical AVN Treatment
AVN treatment without surgery may be considered for selected patients, particularly when the femoral head has not collapsed or surgery is not appropriate at the current time.
Pain Management
Pain-relieving medicines, including non-steroidal anti-inflammatory drugs (NSAIDs), may help manage symptoms when prescribed appropriately. Their suitability depends on your medical history, other medicines and possible side effects.
Protected Weight-Bearing
Reducing the load on the affected hip may help manage discomfort. A walking stick or crutches may be recommended according to the extent of bone damage and your ability to walk.
Your doctor or physiotherapist can explain how much weight you should place on the affected leg.
Guided Physiotherapy
Physiotherapy for AVN may help maintain joint movement, improve muscle strength and support mobility. Exercises should be selected according to the stage of the condition and your symptoms.
High-impact activities may need to be avoided when the bone is structurally weakened.
Risk-Factor Management
Your doctor may discuss reducing alcohol consumption, reviewing corticosteroid treatment with the prescribing clinician and managing relevant medical conditions.
Selected Medicines and Emerging Treatments
Some medicines and biologic approaches have been studied for AVN, but the evidence and suitability vary. These treatments should not be considered established cures or substitutes for appropriate medical assessment.
Non-surgical management may help control symptoms and reduce stress on the joint, but it cannot reliably restore bone tissue that has already died or reverse established collapse. Regular follow-up is important to monitor changes.
Can Stage 3 AVN Be Treated Without Surgery?
Stage 3 AVN treatment without surgery depends on the extent of structural damage, the size and location of the affected area, pain severity and the condition of the hip joint.
Non-surgical measures may help manage symptoms and reduce stress on the hip. However, they cannot reverse an established collapse.
Some patients may be candidates for selected procedures, while others with substantial joint damage may benefit more from hip replacement surgery. The treating surgeon can explain the likely benefits, limitations and risks after reviewing your scans.
Surgical Treatment for AVN
AVN surgery may be considered when the expected benefits outweigh the risks and non-surgical management is insufficient or unlikely to meet the patient’s needs.
The choice of procedure depends on whether the femoral head is intact, the amount of bone damage and the condition of the joint cartilage.
Core Decompression Surgery for AVN
Core decompression for AVN is a joint-preserving procedure in which a small channel is created in the affected bone to reduce pressure and potentially support healing responses.
Who may be suitable?
Core decompression is generally considered for selected patients with early-stage AVN before significant femoral-head collapse.
What is the goal?
The aim is to relieve symptoms and potentially delay progression or the need for hip replacement in suitable cases.
What are the limitations?
Results vary according to the extent of the lesion and the stage of AVN. Core decom
In selected cases, additional techniques such as bone grafting or bone marrow-derived treatments may be discussed. Their suitability and supporting evidence vary.
Bone Grafting for AVN
Bone grafting for AVN involves placing bone material into the damaged area to support the joint surface and help the bone heal. Some techniques use bone that keeps its own blood supply, known as a vascularised bone graft.
Who may be suitable? Selected patients, often younger, with a larger lesion and little or no collapse may be considered.
What are the limitations? It is a more involved procedure and usually needs a period of protected weight-bearing. Results vary, and it may not be suitable once the joint is badly damaged.
Osteotomy for AVN
Osteotomy reshapes and realigns the bone so that body weight falls on healthier areas of the femoral head. It is generally considered for carefully selected, usually younger, patients with a well-defined area of damage.
Recovery can be long, and the procedure is not suitable for every patient.
Total Hip Replacement for AVN
Total hip replacement for AVN replaces the damaged joint surfaces with an artificial implant. It is usually considered when the femoral head has collapsed, pain is significant and arthritis has developed.
Because AVN often affects younger adults than ordinary arthritis, the implant type and bearing surface are discussed individually. Read more about hip replacement surgery in Navi Mumbai. If an earlier implant has worn or loosened, revision hip replacement may need to be considered.
Recovery After AVN Treatment
Recovery depends on the procedure, your age and your general health. The table gives general guidance only, and your surgeon will explain a personal plan.
| Treatment | Typical Early Recovery |
|---|---|
| Non-Surgical Care | Ongoing, with physiotherapy and follow-up scans. |
| Core Decompression | Protected walking for several weeks, as advised. |
| Bone Grafting or Osteotomy | Longer period of protected weight-bearing. |
| Total Hip Replacement | Many patients walk with support within a day or two, with a gradual return to routine over weeks. |
Follow your physiotherapy plan, attend all follow-up visits and avoid alcohol unless your doctor advises otherwise.
AVN Treatment Success Rate
The success rate of AVN treatment depends on the stage at diagnosis, the size of the damaged area, the cause, your age and whether triggers such as steroids or alcohol continue. Joint-preserving treatment generally has a better chance in early stages. After collapse, hip replacement is a dependable option for lasting pain relief. A realistic outlook is possible only after an examination and MRI.
Prevention and Lifestyle Advice
- Limit alcohol intake.
- Use corticosteroids only as prescribed and review long courses with your doctor.
- Get hip injuries and persistent groin pain checked promptly.
- Manage cholesterol and blood sugar, and avoid smoking.
- If one hip has AVN, ask whether the other hip should be checked.
Consult an AVN Specialist in Nerul, Navi Mumbai
Looking for an AVN specialist in Navi Mumbai? Dr. Abhay Chhallani reviews your symptoms and scans, explains your stage in simple language and discusses suitable options without recommending surgery that is not needed. Patients visit from Nerul, Seawoods, Vashi, Kharghar, Belapur, Panvel and Airoli. You can read patient testimonials or book a consultation. Please bring your previous scans, reports and a list of current medicines.
Book an Appointment for Avascular Necrosis
Frequently Asked Questions About AVN
Can avascular necrosis heal on its own?
Rarely. Very small early lesions may stay stable, but AVN usually progresses without proper care, so monitoring is important.
Does every AVN patient need hip replacement?
No. Hip replacement is mainly considered for collapsed joints or advanced arthritis. Many early cases can be managed with joint-preserving treatment.
Is walking safe with AVN?
Usually yes, within limits set by your doctor. High-impact activity is best avoided.
Can AVN affect both hips?
Yes. Bilateral AVN is common, so the other hip may also be checked with an MRI.
Does stopping alcohol or steroids reverse AVN?
It cannot undo existing damage but may help prevent more. Never stop prescribed steroids without medical advice.
Is AVN the same as arthritis?
No. AVN is bone damage from reduced blood supply, though a collapsed joint can develop arthritis later. See inflammatory arthritis of the hip for a different cause of hip joint pain.
Can AVN affect the knee?
Yes, though the hip is more common. Knee AVN can resemble knee arthritis, so imaging helps tell them apart.
Which doctor treats AVN?
An orthopaedic surgeon experienced in hip preservation and joint replacement.